Tampilkan postingan dengan label purple fuzz. Tampilkan semua postingan

Senin, 05 Maret 2012

Does Botox Change The Shrink?


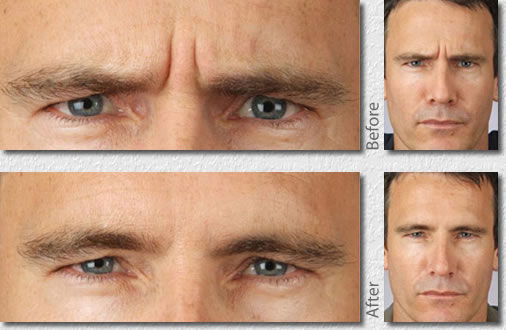
So I'm a little older than I used to be and recently when I look in the mirror, I've noticed some lines in my forehead when I make specific expressions.  I'm not so sure I like them; when they show up in photos, they definitely make me look older.  And yet, I know that these lines aren't just from aging, they are an occupational hazard.  Part of attentive listening in psychotherapy involves using your face to convey, in non-verbal ways, obviously, feelings and expressions and interest and even questions.  These are my quizzical lines.  Really?  Don't you think you're kidding yourself there?  Give me a break.  Not a word gets uttered, but oh so much gets communicated in silence, with the movement of just a few muscles.  Yes, Clink, here and there I have a moment of silence.   A short moment, but still.  Wrinkles as an occupational hazard.  


Every now and then I have the thought that maybe I should Botox those lines away, but my first thought is always, will it interfere with my work?  Who am I as a healthy without the Quizzical Look?  Will my patients relate to me differently?  Will they have worse/different/better therapeutic outcomes if my facial muscles are paralyzed?   Oh, and since they came from my work, can I tax deduct the cost of botox treatments?  


No worries, I'll stay wrinkled....or quizzical....as long as Clink continues to be a nun look-a-like and Roy remains a geek. 

Sabtu, 24 September 2011

Moving Right Along Now

Sent to us from TigerMom and Jay at Two Women Blogging-- which is oddly enough a blog by three women (all that education and they can't count???-- and shamelessly stolen off BoingBoing

Nails painted like anti-depressants

Photo-17
Erin Simon had NYC's Marie Nails In Soho paint her nails like a variety of anti-depressants! (Thanks, Heather Sparks!)

david pescovitz

Comments for this page are closed.

Showing 11 comments


  • Why do i have the sudden urge to play Dr. Mario?
  • UnnecessaryUmlaut 09/16/2011 12:05 PM
    I don't think the white pinky nail is for Zoloft.
  • HenryPootel 09/16/2011 12:06 PM
    You know this could be an interesting placebo.  Just suck on the finger that's got the meds you need. Maybe put Viagra on the ring finger.
  • I think they're suppositories....
  • Seems symbolic since some people chew their nails when anxious or depressed.
  • facetedjewel 09/16/2011 12:25 PM
    Not being able to grow your own long, strong nails and feeling you have to wear fake ones *is* depressing. Symbolic of both cause and remedy.
  • Private Private 09/16/2011 01:28 PM
    I think I know why she's obsessed with anti-depressants. With nails that long, she'd have a hard time, uh, making the most of her natural dopamine highs, if you know what I mean. Wink wink, nudge nudge. Ouch.
  • I think this lady is depressed because of the way her hands look. Chicken, egg?
  • i suppose this is supposed to be "cute" or "wacky," but i find it highly offensive.  sorry.  there's nothing delightful about having one's quality of life (or some semblance of going through the motions of life, anyway) dependant on those horrible pills.
  • I don't know.  It takes a quite a few horrible pills to make me into a functioning member of society and I've made earrings out of most of them.  Sometimes it's better to laugh than cry.
  • You go Jamie Sue.... i don't know why hater's even bother to comment.... it's entertainment... nothing more, nothing less. for anyone to feel "offended" is their issue. Maybe they need to check out the pill selection on her left hand middle finger....... # yaknowhatimean

Sabtu, 02 Juli 2011

Guest Blogger Dr. Andrew Angelino on AIDS, Russia, and Collaboration in Medicine

Every month, the president of our state psychiatric society writes a column for the newsletter.  This month, I read it and thought the column, directed only at healthys, would make a good Shrink Rap post.  Dr. Angelino has graciously allowed us to reprint his article:


“I’d like to talk to you about this patient….”
Some presidents follow a format for these columns.  I have nothing against formats except that I hate them for their…well, “formatness.”  The way I see it, I get to write to you all about 10 times this year and they’ll print what I write pretty much for free and without question, as long as I make some degree of sense and don’t embarrass myself or the profession too much.  So, what I’m really trying to say here is, I hope you enjoy what I have to say. I hope it makes you think a little, and more importantly, I hope it makes you want to talk to another healthy a little, because that’s my goal as your president – to get you involved in the conversation.
I just got back from Russia.  I spend about a week or two a year teaching AIDS Psychiatry in various cities in Russia.  Nowhere glamorous.  Usually, I get to go deep into Siberia in the middle of winter and freeze off body parts.  Although, there is something to be said for opening a conversation with “The last time I was in a Siberian prison….” 
AIDS Psychiatry is an interesting little niche.  Basically, I see patients with HIV infection who have mental health problems.  For the most part, people think that the role of the healthy in this area is mostly dealing with grief or other adjustment issues – basically talking to folks about their concerns over having a life-threatening infection.  Slightly more sophisticated, some recognize that the action of HIV in the brain causes mental problems – dementia and major depression are examples.  But what many don’t think about is that HIV infection is an outcome of mental illness.  That the reason we have such a high concentration of individuals with mental illnesses in HIV clinics is that their mental illnesses render them vulnerable to behaviors that lead to outcomes like HIV, hepatitis, imprisonment, homelessness and other disenfranchisements.  And once they’re infected with HIV, we have complex mentally ill patients that now have to try to manage a life threatening infection along with their mental illnesses.  Basically, that’s my job: help the most vulnerable manage an incredibly difficult task, for the rest of their lives.
Now I’m not telling you this to toot my own horn.  I’m telling you because I learned, from a whole lot of firsthand experience, that all this integrated healthcare, medical home, accountable care mumbo-jumbo really works.
In my clinic, the healthys work in rooms next to the medical doctors.  Today in clinic, I spoke to Mark Sulkowski, infectious diseases doc specializing in HIV-hepatitis C coinfection.  We have several patients together.  I know I can knock on his door anytime he’s not with a patient to discuss a patient or the latest new drug for hepatitis C (we have two new protease inhibitors that will likely increase cure rates).  We also have social workers and pharmacists and case managers and primary care docs and OB/GYNs and dermatologists and ophthalmologists and neurologists.  And we all write in the same charts and manage the same patients together.
In Russia, no such system exists.   Last week, we were discussing the tricky problem of managing patients with HIV infection, active tuberculosis, and active injection drug use.  The biggest problem is there is no system.  TB is treated in the TB clinic, HIV in the HIV clinic, and drugs in the “narcology” clinic (which is independent of both psychiatry and general medicine).  And nobody talks to anybody else.  The Russians are fascinated by the stories of how my clinic, and other HIV clinics in the US with some of the same services, manage complex patient issues.  They are in awe of the resources we can bring to bear to overcome a problem like adherence to medications.  And they are also in awe of our commitment to the public health that permits us to take a stand like mandatory TB treatment using directly observed therapy.
At the MPS annual meeting, I made a short speech.  I said I wasn’t going to stand up to say we have a broken health care system because I didn’t believe it, and I still don’t.  I think we have great health care in the US – it’s just not universally very focused.  We’ve let freedom to choose (a really good thing) gum up a system that can, and sometimes does, work wonders. 
And our profession has taken that a step farther.   We’ve lost ourselves a little in psychiatry and forgotten what makes us most useful to our medical family – our ability to influence attitudes and behavior.  We’ve occasionally let our patients excuse behaviors with mental symptoms and allowed them to fail because we sometimes overvalue their free will to choose to ruin themselves. 
We face issues in the approaching health care “reform.”  The same kinds of issues Russia is facing.  Do we remain in silos and let patients fail because they don’t integrate for us, or do we step into each other’s spaces and learn to co-manage difficult cases?  Do we let payors divide us and limit our work together, or do we strive to demonstrate how effectiveness in one compartment can have benefits in another, thus balancing out for the “whole patient?”  Do we become so specialized in our area that others with no medical training threaten to replace us because they are willing to work cheaper, or do we demonstrate the enhancement medical training has on our ability to integrate with our medical colleagues?
Every time we pick up the phone to talk to the patient’s primary care physician, we integrate health care a little more.  Every time we fax over a note, or send a short (encrypted) email, we integrate a little more.  Shared access to an electronic medical record between Emergency Department doc and healthy?  You bet that’s integration.  And you’re already doing it all the time, I know.  So this “reform” should be a breeze, right?    I guess that’s why I can spend some of my time working on the Russian problem.
Minggu, 26 Juni 2011

Understanding the Research on Psychotherapy Trends-- a Discussion with Dr. Ramin Mojtabai


For whatever reason, it bothers me when media says that healthys don't do psychotherapy, and lately, it happens a lot.  What am I, chopped liver?
They quote a study by Mojtabai and Olfson in the Archives of General Psychiatry, and say, "Only 10.8% of healthys see all of their patients for psychotherapy."  Is that really true?  Is it really relevant?  I tried to read the article and I wanted to understand how the study was done so I could think about it myself, but I didn't understand how the research was done-- Roy thought it was based on CPT codes, then he said it wasn't.  So why not go to the source?  I asked Dr. Mojtabai if he would have lunch with me and tell me how the study was conducted.

If that got you curious, please read about it on over on Shrink Rap News!  You're welcome to comment there if you're physician, or to surf back here and tell us what you think.  Ramin says he's interested in what people think, and he's been very kind about humoring me, both over lunch and in the many subsequent emails over the details.

Kamis, 03 Maret 2011

i before e, except after w?


I mean we're shrinks, we deal with the weird everyday. If anyone knows weird, it's us.

So I get this email from Roy.
Stop spelling it "wierd" it's "weird" you have it stuck in your head wrong. He's right and he gave me a long list of places on Shrink Rap where weird is misspelled as 'wierd.' Only they weren't all me. Clink did it a couple of times. Sarebear did it in our comment section. I did it a bunch. This is weird. But it is "i before e except after c"...right? Why is weird spelled weirdly?

Maybe I need a new word. Strange. Unusual. Unconventional. Odd. That's a good one, even I can't spell "odd" wrong.

From Wikipedia:

Old English wyrd is a verbal noun formed from the verb weorþan, meaning "to come to pass, to become". The term developed into the modern English adjective weird. Adjectival use develops in the 15th centrury, in the sense "having the power to control fate", originally in the name of the Weird Sisters, i.e. the classical Fates, in the Elizabethan period detached from their classical background as fays, and most notably appearing as the Three Witches in Shakespeare's Macbeth. From the 14th century, to weird was also used as a verb in Scots, in the sense of "to preordain by decree of fate".

The modern spelling weird first appears in Scottish and Northern English dialects in the 16th century and is taken up in standard literary English from the 17th century. The regular modern English form would have been wird, from Early Modern English werd. The substitution of werd by weird in the northern dialects is "difficult to account for".[1]

The now most common meaning of weird, "odd, strange", is first attested in 1815, originally with a connotation of the supernatural or portentuous (especially in the collocation weird and wonderful), but by the early 20th century increasingly applied to everyday situations.[2]

Enough. It's all too weerd. The chinchilla is for Jesse because his preoccupation with the little rodents is kind of ....different.

Senin, 28 Februari 2011

Like Looking in a Mirror


Sometimes, I treat people who have the same problems I have in my personal life. It's hard. Oh, it's really hard. If I'm really distraught about something and a patient calls seeking treatment with a similar life circumstance, I will sometimes turn them away and recommend another shrink. But I don't always screen so carefully on the phone, and often "I'd like to make an appointment," will simply get a time and date.

The feelings get really complicated here.

If I feel I've had a role in creating my circumstances, then I wonder as my patients seek my counsel, Who am I to be making any suggestions, much less giving advice? Why are you looking to me, I've screwed up the same situations. Oh, you say, Dr. Jeff said on KevinMD that healthy's Shouldn't Give Advice, but you know, some of us do, and even when we don't, our feelings are often relayed through the questions we ask or the comments we make or don't make, or perhaps by the expressions on our faces, even if we don't say "You
should do X." I told a friend once that I feel uneasy, guilty even, in these situations, and he replied, "How do you think I feel?" Did I mention he does family work and was in the midst of a stressful divorce? And I have yet to ask a colleague who also does family work how he managed during the years his own children wouldn't speak to him. Oy, life can be tough, for shrinks just like everyone else.

So perhaps I listen to someone talking about his most personal feelings about a situation, and you know, if I've been there before, perhaps it's good that I can empathize. If I'm in the middle of it, sometimes I listen and the patient's words seem so unreasonable, so unjustified, and yet I recognize them as being exactly my own--it's like having my own anxieties bounced off a wall only to ricochet straight back into my face.

Do I tell the patient that I've been in the same place before? Generally, no. Therapy is about his problems, not mine, and I think in these situations my empathy is clear. I say things that are more poignant and resonant than I might in circumstances where I feel removed. And patients never ask if I've been in the exact same place. On some of the harder things-- things that have no precise quick and easy answer-- I've taken to saying, "Not only don't I know what will fix this, I don't know anyone else who does have the answer." This I can say because I've done my own searching.

I hope I'm reassuring and comforting to people who find themselves in the same places I dwell. Certainly, tripping over a few stones on the path makes one walk a little more gingerly and judge a little less harshly those who walk more slowly. Mostly, though, I worry that I'm a little bit of a fraud just for being in the room.